Living with a sensory-seeking toddler can feel utterly exhausting. Endless chasing from morning to night, with a child constantly in motion and seeking input. Fear that their intensity will lead to physical harm, emotional outbursts, or meltdowns in public places can make even the most mundane daily activities challenging.
When pediatricians dismiss your concerns with “it’s just normal toddler behavior,” but your gut tells you something’s different, trust that instinct. We’ll explain how Sensory Processing Disorder produces the neurological imbalances behind sensory craving, what you can do at home starting today, and why addressing the root cause matters more than managing the behavior.
A sensory-seeking toddler is a child between roughly 12 months and 3 years old whose nervous system has a high sensory threshold, meaning their brain under-registers ordinary sensory input. To compensate, they pursue unusually intense movement, pressure, sound, or oral stimulation. In clinical terms, this pattern is called sensory craving, one of three recognized presentations of Sensory Processing Disorder alongside over-responsiveness and under-responsiveness.
What Is a Sensory Seeking Toddler
Sensory seeking falls under a subtype called Sensory Modulation Disorder, in which a child’s brain cannot adequately modulate the intensity or frequency of incoming sensory signals. Around 1 in 6 children experience sensory processing difficulties significant enough to affect daily function, and sensory craving is one of the most common presentations parents bring to us.
At the core of sensory seeking is the concept of sensory thresholds, or how much stimulation a child’s brain needs to register. Children with high sensory thresholds don’t detect sensory information as easily as other children. Their brains need more intense or frequent stimulation through movement, touch, sound, or pressure before they notice or respond. This isn’t about poor behavior. It’s a neurological difference in how the brain processes information from the environment.
When a child has a high neurological threshold, we see what’s called under-registration of input. As a result, these children seek more intense or frequent stimulation to maintain arousal levels and emotional balance. It’s not hyperactivity or defiance. It’s their body trying to self-regulate.
The Eight Sensory Systems
While most people think of the traditional five senses, sensory seeking actually involves eight sensory systems. Beyond sight, sound, taste, smell, and touch, children also process:
- Vestibular input (balance and movement): Housed in the inner ear, it controls spatial orientation and movement detection
- Proprioceptive input (body position awareness): Feedback from muscles and joints about where the body is in space
- Interoception (internal body signals): Awareness of hunger, thirst, need for bathroom, heart rate, and temperature
Sensory-seeking toddlers typically crave input across multiple systems, especially vestibular and proprioceptive, because their brains need more feedback to feel regulated and “just right” in their bodies. Some children have high thresholds across all eight systems, while others seek vestibular input intensely but avoid certain tactile sensations. Knowing which systems your child seeks from is what makes the difference between guessing and actually helping.
What Does Sensory Seeking Look Like in a 1, 2, or 3 Year Old
Toddlers are already wired for exploration and movement, which is developmentally normal. So how do you know when it crosses into sensory craving? The difference isn’t the behavior itself. It’s the intensity, the frequency, and whether your child can stop.
A typical toddler jumps off the couch once for fun, then moves on. A sensory-seeking toddler jumps off the couch 40 times in a row, gets upset when you stop them, and immediately looks for something else to crash into. Their brain isn’t getting the “full” signal that most kids would get after a few jumps.
The presentation shifts across toddlerhood:
- 12 to 18 months: Constant mouthing well past teething, head banging or rocking to fall asleep, throwing themselves backward, resisting being held still for diaper changes
- 18 to 24 months: Climbing everything regardless of height, running rather than walking between rooms, biting or hard hugging other children, spinning without getting dizzy
- 2 to 3 years: Crashing into furniture and people on purpose, chewing shirt collars and sleeves, extreme resistance to transitions, meltdowns leaving the park or getting into a car seat
Across all three stages, watch for movement that doesn’t wind down, decreased pain response after real collisions, and sleep struggles rooted in a nervous system that can’t slow down even when exhausted.
Sensory seeking also sorts by which system a child is chasing:
- Vestibular seekers (movement and balance): Spinning, rocking, head shaking without dizziness, craving swinging and sliding, enjoying being upside down
- Proprioceptive seekers (deep pressure): Crashing and bumping play, firm hugs and tight swaddling, no sense of personal space, tiptoe walking or heavy loud steps
- Oral seekers: Chewing non-food items, shirt collars and sleeves, preferring crunchy or chewy foods, teeth grinding
- Tactile seekers: Constant touching and fidgeting, messy play, seeking textures, decreased sensitivity to pain
- Auditory and visual seekers: Making loud noises, seeking noisy environments, fascination with spinning objects and lights
Some oral behavior fits normal toddler development. Sensory seekers take it well past expected ages. Notably, they find fulfillment in activities other toddlers find frightening, like spinning until nauseous. These behaviors often look like “behavioral problems” to pediatricians and daycare staff. To a trained eye, they point to nervous system dysregulation as the driver, not age-appropriate curiosity.
What’s the Difference Between Sensory Seeking and Sensory Avoiding
Many parents get confused when their child shows both patterns. One moment they’re crashing into furniture, the next they’re covering their ears at normal sounds. This isn’t contradictory. It’s common, and it’s the clearest window into what’s actually happening neurologically.
Sensory seekers have high sensory thresholds. Their brains under-register input, so they crave more intense stimulation to feel regulated. Think of their nervous system’s “gas pedal” as stuck down. Sensory avoiders have low thresholds. They over-respond and quickly become overwhelmed by sounds, textures, lights, or movement others barely notice. Their “brake pedal” is overly sensitive.
Here’s the piece most parents never get explained: you cannot have too little tone in one part of the nervous system without having too much somewhere else. Dr. Tony Ebel describes the two presentations as “raging bull” and “drunken bull” kids. Raging bull children are overstimulated even at rest, hypersensitive to noise, light, and touch. Drunken bull children are understimulated and physically disorganized, struggling with posture, coordination, and gross motor skills like skipping and jumping, and they go after sensory-seeking behaviors to fill that void.
Most sensory-seeking toddlers are primarily drunken bull presentations with raging bull features mixed in. That mix isn’t a contradiction in your child. It’s the signature of dysautonomia, where the Autonomic Nervous System runs too hot in some areas and too quiet in others at the same time.
What Causes Sensory Seeking in Toddlers
We reference “The Perfect Storm™” to describe the accumulation of stressors that interfere with healthy neurological development. For sensory seeking, factors spanning pregnancy through toddlerhood layer together to produce an overactive nervous system unable to calm itself.
The best way to understand the result is to think of air traffic control. The nervous system routes every incoming signal from inside and outside the body, deciding what lands, what waits, and what gets ignored. Researcher A. Jean Ayres has described sensory processing difficulties as a neurological traffic jam, and that’s exactly right. When the tower is jammed, signals don’t stop arriving. They just stop being organized. Dr. Tony calls the result a confused nervous system, and confusion is the honest word for it.
Birth trauma, C-section, and forceps or vacuum delivery can injure delicate neural structures and disrupt neurosensory communication. Fixations of the upper neck and throughout the neurospinal system, called subluxation (misalignment, fixation, and neurological interference together), further reduce communication between brain and body. Research has examined associations between delivery method and sensory processing outcomes in children. Clinically, Dr. Tony Ebel reports that the large majority of sensory cases in PX Docs offices show at least one birth intervention in the case history.
A key piece most parents never hear: the brainstem is the master regulator of sensory processing and arousal. When the upper neck is compromised by birth trauma or subluxation, brainstem function is directly disrupted. The nervous system gets stuck in sympathetic overdrive, which is exactly why sensory seeking shows up alongside sleep disruption, digestive issues, and emotional dysregulation. These aren’t separate problems. It’s one nervous system under stress.
There’s also a sequence worth knowing. Kids with colic often grow into sensory challenges. Kids with sensory challenges often grow into ADHD and anxiety presentations. Add recurring early stressors like ear infections, constipation, repeated antibiotics, or food intolerances, and the pattern compounds. “They’ll grow out of it” points in the wrong direction. They grow into the next thing unless something addresses the foundation.
How Does the Vagus Nerve Affect Sensory Regulation
The vagus nerve is the primary communication highway between brain and body, running from the brainstem through the neck, chest, and abdomen. It’s the master switch for the Parasympathetic Nervous System, the calm-and-connected state. Dr. Tony calls it the great wandering nerve, and out of every sensory nerve in the body, it’s the one that matters most here. It’s overwhelmingly sensory rather than motor, and entirely parasympathetic: calming, resting, integrating, modulating.
When vagus nerve function is compromised, often through upper cervical subluxation following birth trauma, the parasympathetic system can’t do its job. The brain can’t adequately modulate incoming sensory signals. The result is a nervous system stuck in high gear, constantly seeking input to try to achieve what healthy vagal tone would provide automatically. Research confirms that vagus nerve activity measurably affects sensory processing across multiple modalities.
This is why so many sensory-seeking toddlers also struggle with sleep, digestion, and emotional regulation. All three run through the vagus nerve.
Is Sensory Seeking a Sign of ADHD or Autism
Parents of sensory-seeking toddlers are often eventually told their child may also have ADHD or be on the autism spectrum. Sensory processing differences are present in up to 90% of children with autism, and a significant share of children with ADHD show sensory modulation differences as well.
From a neurological standpoint, this makes sense. ADHD, autism, and sensory craving all involve disruptions in how the nervous system processes and regulates incoming information. They share a common root in a dysregulated Autonomic Nervous System. Broadly, the overstimulated raging bull pattern tends to track toward hyperactive ADHD presentations, while the understimulated drunken bull pattern, the one most sensory seekers fall into, tends toward attention, focus, and emotional regulation challenges.
This is why we look beyond the label. Whether a child carries a diagnosis of Sensory Processing Disorder, ADHD, or autism, or all three, the starting point is the same: assess the nervous system, identify the dysfunction, address it at the source. Labels describe the behavior. They don’t explain the cause.
When Should You Worry About Sensory Seeking
Not all sensory seeking is concerning. Adaptive sensory seeking helps children self-regulate. Jumping on a trampoline before a quiet activity, chewing on a safe oral tool, or asking for bear hugs when stressed are healthy strategies that give the nervous system what it needs.
Maladaptive seeking creates safety risks or significantly disrupts daily functioning:
- Jumping from dangerous heights without recognizing risk
- Hitting or crashing into peers for proprioceptive input
- Constant disruption of family routines and daycare activities
- Difficulty sitting for meals or car rides
- Social isolation because the intensity overwhelms other children
- Frequent injuries, often with a muted pain response
Unmet sensory needs can also lead to sensory overload and meltdowns, difficulty focusing in structured settings, sleep challenges, and in some cases delayed speech and language development.
The line isn’t the behavior itself. It’s whether your child can access the input they need safely, and whether the seeking is interfering with learning, relationships, and daily life. Many parents describe feeling isolated, judged, and dismissed with “they’ll grow out of it.” Those instincts deserve better than reassurance.
How Can You Help a Sensory Seeking Toddler at Home?
You don’t have to wait for an evaluation to start giving your toddler’s nervous system what it’s asking for. The goal isn’t to stop the seeking. It’s to redirect it into safe, organized input.
- Give them a yes space. Set up floor pillows, gym mats, beanbags, or an old couch cushion crash pad where crashing and jumping are allowed. Sensory seekers need somewhere the answer isn’t “stop.”
- Lean on heavy work. Activities that make muscles push or pull against resistance are the most organizing input you can offer. Have your toddler push a laundry basket, carry grocery items, pull a wagon, help move chairs, or do wall push-ups. Heavy work delivers deep joint input directly to the proprioceptive system.
- Build in movement before stillness, not after. Ten minutes of jumping, swinging, or animal walks before meals, car rides, or bedtime works far better than trying to settle an already-escalated toddler. Rhythmic, back-and-forth linear swinging tends to calm, while spinning tends to rev up.
- Give structure a start and a stop. This one matters most for toddlers. Sensory seekers will keep going until they’re over-aroused and dysregulated, so cap activities: swing to a count of ten, then hop off and put a toy in a basket. A visual timer and a designated “waiting spot” between activities do more for transitions than any single tool.
- Redirect oral seeking rather than fighting it. If your toddler chews collars and sleeves, their mouth is asking for input. Safe chew tools, crunchy foods, thick smoothies through a straw, and water bottles with resistance valves meet the need. Chewing usually eases when that input is available.
- Try deep pressure, and read the response. Firm bear hugs with consent, rolling a therapy ball along the back, being squished between cushions, or a snug sleep sack can be very regulating. Discuss weighted products with your pediatrician or occupational therapist before using them with a toddler.
Track what actually helps and what backfires. That log becomes some of the most useful information you can bring to any provider.
How Is Sensory Seeking Assessed and Addressed at the Root
Many parents turn to occupational therapy first, and it helps. A sensory diet, a personalized plan of daily activities matched to your child’s profile, can meaningfully improve daily function, and a skilled pediatric OT will teach you which heavy work and oral tools fit your specific child. OT, PT, and speech are movement-based therapies, and movement is genuinely the right access point.
What Dr. Tony hears constantly, though, is families who did months or years of movement-based therapy, changed the diet, changed the clothes, and put the sensory gym in the basement, and still saw their child plateau. Real changes, but partial ones. That plateau is the clue. It points to a deeper neurological dysfunction beneath the altered motor tone, which is why the nervous system itself must be measured rather than inferred from behavior.
This is where INSiGHT scanning technology, developed and owned by the Chiropractic Life Alliance, becomes valuable for parents seeking answers. It’s important to note that this technology does not diagnose medical conditions, and Neurologically-Focused Chiropractic Care is certainly not a treatment or cure for sensory-seeking behavior or any other condition, not even back pain.
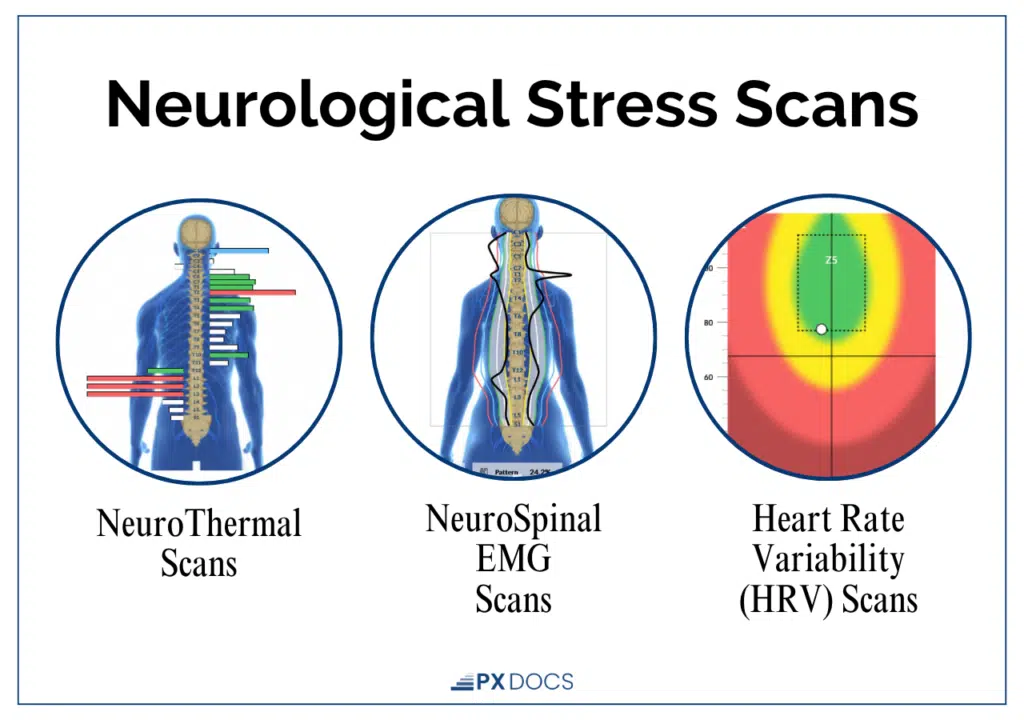
Instead, these INSiGHT Scans help us track down the root cause of nervous system dysfunction and dysregulation, and build customized care plans and adjust protocols to help shift the nervous system back into a state of balance, regulation, and resilience. Surface EMG maps where neuromotor tone is excessive and where it’s exhausted. Heart rate variability shows whether the Autonomic Nervous System is sympathetic-dominant or depleted and gives an objective read on vagal tone. As Dr. Tony puts it, we don’t guess. We test.
Through our Clinical Process, we:
- Take a detailed case history examining prenatal stress, birth trauma, and early childhood stressors
- Run baseline INSiGHT scans to objectively measure nervous system function and locate subluxation and dysregulation patterns
- Build a customized care plan targeting the specific patterns affecting your child’s sensory processing
- Apply gentle, precise adjustments to release stuck sympathetic tension and support vagus nerve function
- Re-scan to track progress so changes in nervous system function are measured, not assumed
Finding Help for Your Sensory Seeking Toddler
If the scans show what we’d expect, the plan moves forward. If they don’t, that’s useful information too, and it points you somewhere else rather than into months of care that wasn’t the right fit.
If you’re exhausted, have tried conventional approaches without lasting results, or your gut says something deeper is going on, we encourage you to explore Neurologically-Focused Chiropractic Care.
The Perfect Storm that shaped your child’s sensory challenges didn’t happen overnight, and healing takes time. But by addressing subluxation and nervous system dysfunction rather than only managing the behavior, you give your child’s body the opportunity to regulate naturally. Find a PX Doc near you through our Directory and take the first step toward understanding what’s really driving your child’s sensory seeking.
Your instinct that something deeper is happening? Trust it. And know that help is available.