


Proprioceptive stimming is repetitive movement a child uses to feed their brain the body-position and movement signals it doesn’t get enough of on its own. Jumping, crashing, stomping, hand flapping, toe walking, teeth grinding, and chewing all deliver proprioceptive input, the sensory information that muscles and joints send to the brain about where the body is in space. When that input runs low, the nervous system shifts toward stress, and the child compensates by generating movement themselves. Proprioception stimming is not a bad habit, and it is not a choice. It is a nervous system trying to calm itself.
If you’ve ever watched your child flap their hands, rock back and forth, or grind their teeth and wondered whether it’s cause for concern, you’re asking the right question. These self-stimulatory behaviors, or “stimming,” are common in children with Autism Spectrum Disorder, and they have a real neurological explanation.
Take Joseph, for example. Joseph came to our clinic in October of 2022 for a 2-week Neuro Intensive Program, struggling every day with the neurological effects of Autism, anxiety, constipation, and gross motor skills challenges. Watching him become calmer with each adjustment was incredible. The tension in his shoulders and arms relaxed almost immediately, and his stimming dropped significantly within days. Instead of anxiety and tension, he was smiling and eager to work out. In two weeks, he made remarkable progress, and he continues care at home with another Neurologically-Focused PX Doc today.
The Roots of Autism Stimming
As a parent, it’s natural to feel unsure about what stimming means and how to respond. You might have been told it’s just a quirk your child will outgrow. But stimming serves a purpose. It helps children cope with overwhelming sensory input, express emotion, and self-regulate.
A survey of adults on the Autism spectrum found that approximately 80% said stimming reduces their anxiety and helps them calm down. That’s a striking number, and it reframes the whole conversation. Stimming isn’t the problem. It’s the solution your child’s nervous system came up with on its own.
Here’s something I emphasize every time I teach this topic: stimming is not a conversation only for families with an Autism diagnosis. The same neurological pattern shows up in Sensory Processing Disorder, ADHD, anxiety, and PANS/PANDAS. It shows up in adults, too. Ever been so wound up that you had to crack your own neck, or get up from your desk and move because you couldn’t sit still another minute? Same mechanism, different intensity. Restless legs, nail biting, and teeth grinding are adult stims.
What makes it harder for kids on the spectrum is that their nervous system is already running at capacity before the world adds anything to it.

What Does Proprioception Stimming Look Like
Most articles group stims by what they look like. It’s more useful to group them by which sensory system they’re feeding, because that tells you what the nervous system is actually asking for.
Proprioceptive stimming feeds the muscles and joints. This is the deep-pressure, heavy-work category:
- Jumping, stomping, and bouncing
- Crashing into furniture, walls, or people
- Squeezing fists, pushing, or pulling heavy objects
- Hand flapping and finger flicking
- Toe walking
- Teeth grinding, chewing on shirts, pencils, or jewelry
- Seeking tight hugs, weighted blankets, or being squeezed
- Head banging or head hitting
Vestibular stimming feeds the balance system: spinning, rocking, swinging, hanging upside down. Proprioception and vestibular input work closely together, which is why rocking often gets miscategorized. The difference is that proprioception involves pressure and resistance through muscles and joints, while vestibular input comes from head position and motion.
Tactile stimming involves touch: rubbing surfaces, scratching, hand-wringing, skin picking.
Oral stimming involves the mouth and jaw: chewing, biting, licking, and lip smacking. Oral stims are technically proprioceptive too, because the jaw is loaded with movement receptors.
Visual and auditory stimming involves staring at lights or spinning objects, lining things up, humming, echolalia, or replaying the same song, show, or book on repeat.
Stimming in Autism tends to be more frequent, more intense, and harder to stop than the self-soothing habits most people have. A child may also experience “happy stimming” as a way to express joy. It’s worth saying plainly: children can’t control it, and they don’t want to do it. This is not a conscious decision to grind teeth or chew a shirt collar.
Why Proprioceptive Input Calms an Overwhelmed Nervous System
Think about a day when you sat for hours. Commute, desk, commute home. By the end of it, are you calmer and more focused, or do you need to get up and move before you lose your mind? Now imagine you stop at the gym or take a walk before dinner. You come home settled.
That’s proprioception doing its job.
Proprioception is defined as the sensory perception of movement. Every time a muscle contracts or a joint loads, receptors fire signals up into the brain. Those signals travel to the cerebellum, which acts as air traffic control for movement, then to the thalamus, hippocampus, amygdala, and finally the prefrontal cortex. The cerebellum needs a steady stream of movement input to stay calm, organized, and connected to the rest of the brain.
Proprioception is the good side of the sensory equation. It’s inherently calming.
So when a child’s nervous system is overstimulated and not getting enough of that calming input from the inside, they have to overcompensate and manufacture it from the outside. That’s proprioception stimming. The jumping, the crashing, the chewing, the flapping- all of it is the body generating the movement signals the brain is starving for.
Research supports the underlying deficit. A study of children with Autism using standardized proprioceptive testing found diminished proprioception and increased pain sensitivity compared to typically developing peers. Earlier work using the Comprehensive Observations of Proprioception documented a distinct pattern of proprioceptive processing difficulty in children with Autism Spectrum Disorder and other developmental disabilities.
This is also where proprioception stimming and sensory seeking overlap. A sensory seeker actively hunts for input across the day. Proprioception stimming is narrower and more repetitive, and it tends to spike when the nervous system is already overwhelmed. Many kids do both.
Which Parts of the Body Are Most Proprioception-Rich
Here’s the piece almost every article on stimming misses, and it’s the one that explains why your child stims where they stim.
Proprioceptive receptors aren’t spread evenly through the body. Some regions are far more densely packed than others. In order of density, the most proprioception-rich zones are:
- The neck and brainstem, particularly the occiput and the top two vertebrae (the atlas and axis). This region isn’t close to second place. It’s the single most movement-sensitive area of the body.
- The jaw
- The hands and feet
- The genitals
Now look at that list next to the list of common stims. Teeth grinding and chewing. Hand flapping and finger flicking. Toe walking. Inappropriate touching. Those aren’t random behaviors. They’re the next-densest proprioceptive zones the body can reach when the densest one, the neck, isn’t delivering.
It also explains a set of things parents notice long before anyone mentions stimming. Kids who hate haircuts. Kids who can’t stand having their neck or ears touched. Kids who fight teeth brushing. That resistance clusters right around the most proprioceptively loaded real estate in the body.
The neck’s role here isn’t just clinical observation. In adults with Autism, researchers induced a postural illusion using vibration applied to the posterior neck muscles alone, and found the participants didn’t correct for it with vision the way typically developing adults did. That study was conducted in adults, so it doesn’t tell us how children would respond, but it does confirm how powerfully neck proprioception drives whole-body position sense.
Clinically, I see head banging and head hitting showing up most in children carrying upper cervical brainstem tension from birth trauma like forceps, vacuum extraction, emergency C-section, or cord wrapping. These kids are, in a very literal sense, trying to adjust themselves.
The Neurological Roots of Stimming in Autism
Underneath all of this sits an imbalance in the Autonomic Nervous System, the part that runs heart rate, digestion, and breathing without you thinking about it. It has two branches, and the easiest way to picture them is a gas pedal and a brake pedal.
- The sympathetic nervous system is the gas pedal, firing up “fight, flight, or freeze” under stress
- The parasympathetic nervous system is the brake pedal, handling “rest, regulate, and digest”
In Autism, the gas pedal is often stuck down while the brake pedal barely works. That imbalance is called dysautonomia, and it leaves a child in chronic hyperarousal and sensory overload, unable to downshift.
The Vagus Nerve and the Brake Pedal
The vagus nerve is the longest cranial nerve in the body and the main hardware behind that brake pedal. When it’s working well, it promotes calm and safety and lets a child self-regulate. In many children with Autism, it’s underactive or effectively stuck, unable to counter the sympathetic side.
I call the sequence that gets a nervous system into this state The Perfect Storm™, and it unfolds in three stages:
- Prenatal stress, including fertility challenges, maternal stress and trauma during pregnancy, and stress hormones crossing the placenta
- Birth interventions and trauma, including C-section, forceps, vacuum extraction, induction, and prolonged labor, which physically load the brainstem, upper neck, and vagus nerve
- Early childhood stressors, including antibiotics, environmental toxins, chronic medication use, and recurring illness
Each stage compounds the last, producing the nervous system dysregulation that eventually surfaces as stimming and other challenges. Critically, the same storm that dysregulates the autonomic system also locks tension into the neck and brainstem, the exact region proprioception depends on most.
How Proprioception, Nociception, and Dysponesis Work Together
The mechanism connecting all of this runs through subluxation. Subluxation has three components that always occur together:
- Misalignment of the joints of the skull, jaw, neck, or spine
- Fixation, meaning those segments lose normal movement
- Neurological interference, meaning altered sensory signaling and tension through the neurospinal system
That third component is the one that matters most here, and it’s the one conventional care never looks for.
When subluxation locks into the upper neck and brainstem, it decreases proprioception coming out of that region. And proprioception and nociception operate on a gate. Nociception is the nervous system’s perception of noxious, stressful, or potentially harmful stimuli. When proprioception drops, the gate opens and nociception climbs.
That’s exactly the pattern the pediatric research found: diminished proprioception alongside heightened pain sensitivity in the same children.
The result is a disorganized, inefficient pattern of neuromuscular activity known as dysponesis, which pushes the Autonomic Nervous System further into sympathetic dominance and further degrades sensory processing. The child stims harder, which is the only lever they have.
I describe what happens next with an analogy worth sitting with. Nerves that fire together wire together, which is the principle behind muscle memory. It works beautifully when a child is learning an instrument. It works against them here. Stimming gets grooved in like a scratch on a CD. Every time the system comes around to that spot, it skips. The path stops being smooth, and over time the child needs more stimming to get the same calming effect. That’s why families who have tried everything still feel stuck.
Does your child’s stimming ever look like they’re worried they’ll be harmed? Like they’re in full fight-or-flight, needing to touch something or move a certain way just to feel safe? If that’s what it looks like emotionally, that’s what’s happening neurologically.
Finding Dysponesis on NeuroCore sEMG Scans
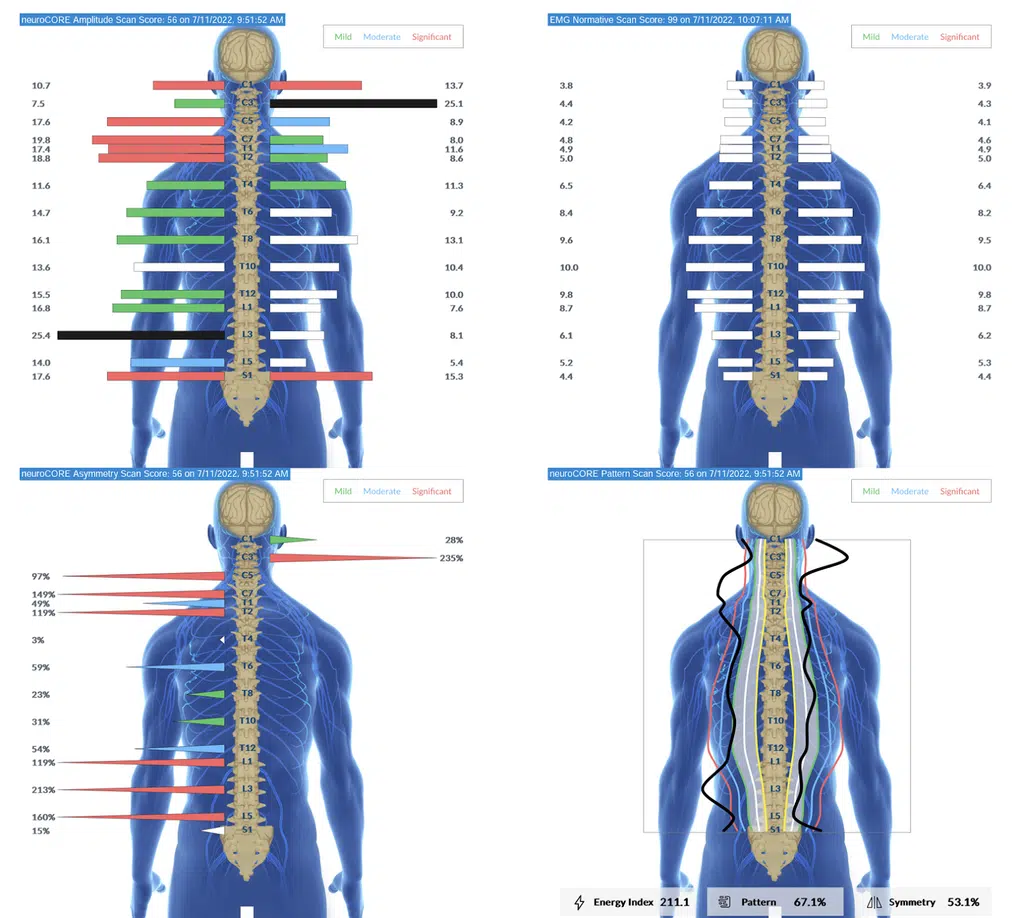
The images above come from the NeuroCore surface EMG scan, part of the INSiGHT scanning suite developed by the Chiropractic Leadership Alliance (CLA) and used in PX Docs offices. This child’s scan shows excessive tension, hypertonicity, and nociception in the green, blue, red, and black regions, and the bottom left scan shows the significant asymmetrical subluxation and tension pattern we see very commonly with stimming.
How PX Docs Get to the Root Cause of Proprioception Stimming
We don’t guess. We test.
The first step is measuring how the nervous system is actually functioning, using INSiGHT scans. These non-invasive scans use three technologies: heart rate variability to assess autonomic balance, surface EMG to map neuromuscular tension and dysponesis, and thermal scanning to detect autonomic regulation patterns along the neurospinal system.
Together they reveal:
- Areas of subluxation and neurological interference within the neurospinal and neurosensory system
- Patterns of autonomic imbalance such as sympathetic dominance or vagal withdrawal
- Objective markers of sensory processing dysfunction
It’s important to note that this technology does not diagnose medical conditions, and Neurologically-Focused Chiropractic Care is certainly not a treatment or cure for Autism or any other condition, not even back pain. Instead these INSiGHT Scans help us track down the root cause of nervous system dysfunction and dysregulation, and build customized care plans and adjusting protocols to help shift the nervous system back into a state of balance, regulation, and resilience.
Repeat scans through the course of care show whether the system is genuinely reorganizing. If the data says we’re on track, we keep building. If it says something needs to shift, we adjust the plan.
What Parents Can Do About Proprioception Stimming
The goal is not to eliminate stimming. Stimming is how your child copes. The goal is to reduce how much they need it, by improving what their nervous system can do on its own.
Signs stimming has crossed into territory worth addressing:
- It interferes with learning, socializing, or daily activities
- It’s causing physical harm, such as head banging or self-biting
- It’s affecting your child’s self-esteem or relationships
Give the proprioceptive system what it’s asking for. Heavy work is the most direct route: carrying groceries, pushing a laundry basket, animal walks, wall pushes, monkey bars, trampoline time, resistance bands, chewy snacks, and weighted blankets. Building this into the day before overwhelm hits works far better than reaching for it mid-meltdown.
Adjust the environment. Reduce visual clutter and noise, offer a quiet space to retreat to, avoid flickering fluorescent lights, remove scratchy tags and seams, and keep routines predictable.
Build self-regulation skills. Visual schedules for transitions, naming emotions, deep breathing, and regular movement breaks all help, and modeling your own regulation matters more than any of them.
Get the sequencing right. This is the part almost nobody tells parents. If your child is doing primitive reflex work, vestibular therapy, vision therapy, and biomedical protocols all at once and things are getting worse rather than better, it may be too much for a nervous system that’s already destabilized. I’ll be direct about this: sometimes doing less achieves more. Foundational nervous system work comes first, and other interventions land better once the system has some slack in it.
It’s also worth knowing that stimming sometimes temporarily increases when a child begins movement-based care. This can reflect a reorganizational healing response, where the nervous system revisits developmental steps it skipped. A skilled clinician can tell the difference between that and doing too much at once, which is a conversation worth having with your provider rather than guessing.
Build the right team. Occupational therapists identify sensory triggers and build coping strategies. Speech therapists work on functional communication. Adding a Neurologically-Focused Pediatric Chiropractor addresses the layer underneath: the subluxation and neurological interference driving the dysregulation in the first place.
If you’ve already worked through the environmental modifications and traditional therapies and your child’s stimming hasn’t budged, that’s a strong signal the root cause sits deeper in the neurospinal system.
A Path to Thriving
Stimming has been dismissed for too long as a meaningless quirk or misbehavior. It’s neither. It’s a nervous system doing exactly what it needs to do to survive an environment it can’t yet filter.
Once you understand proprioception stimming for what it is- an attempt to generate calming movement signals the brain isn’t receiving on its own- the whole picture changes. You stop trying to stop the behavior and start asking what the nervous system is missing.
The aim of Neurologically-Focused Chiropractic Care isn’t a child who stims less in a carefully controlled room. It’s a child who can handle the noisy waiting room, the birthday party, the airport, and the water park. Not a smaller life, a fuller one.
We encourage you to visit our PX Docs directory to find a provider near you.
The journey isn’t easy, but it’s worth taking, because every child deserves the chance to live a life of joy, connection, and limitless possibility.



